Digestive side effects were common in the STEP trials of weekly injected semaglutide, but the headline percentages answer different questions. Some count people who ever reported a symptom. Others count individual episodes, describe their intensity, or record why treatment stopped. Confusing those denominators can make the same evidence sound either more reassuring or more alarming than it is.
The central evidence is a post hoc analysis of STEP 1–3, with a separate examination of STEP 4. It found more gastrointestinal symptoms with semaglutide than placebo, usually mild or moderate episodes, and substantial weight loss among participants who did not report digestive adverse events. Understanding those findings requires looking beyond frequency to duration, participant selection, and the assumptions behind the weight-loss modeling.
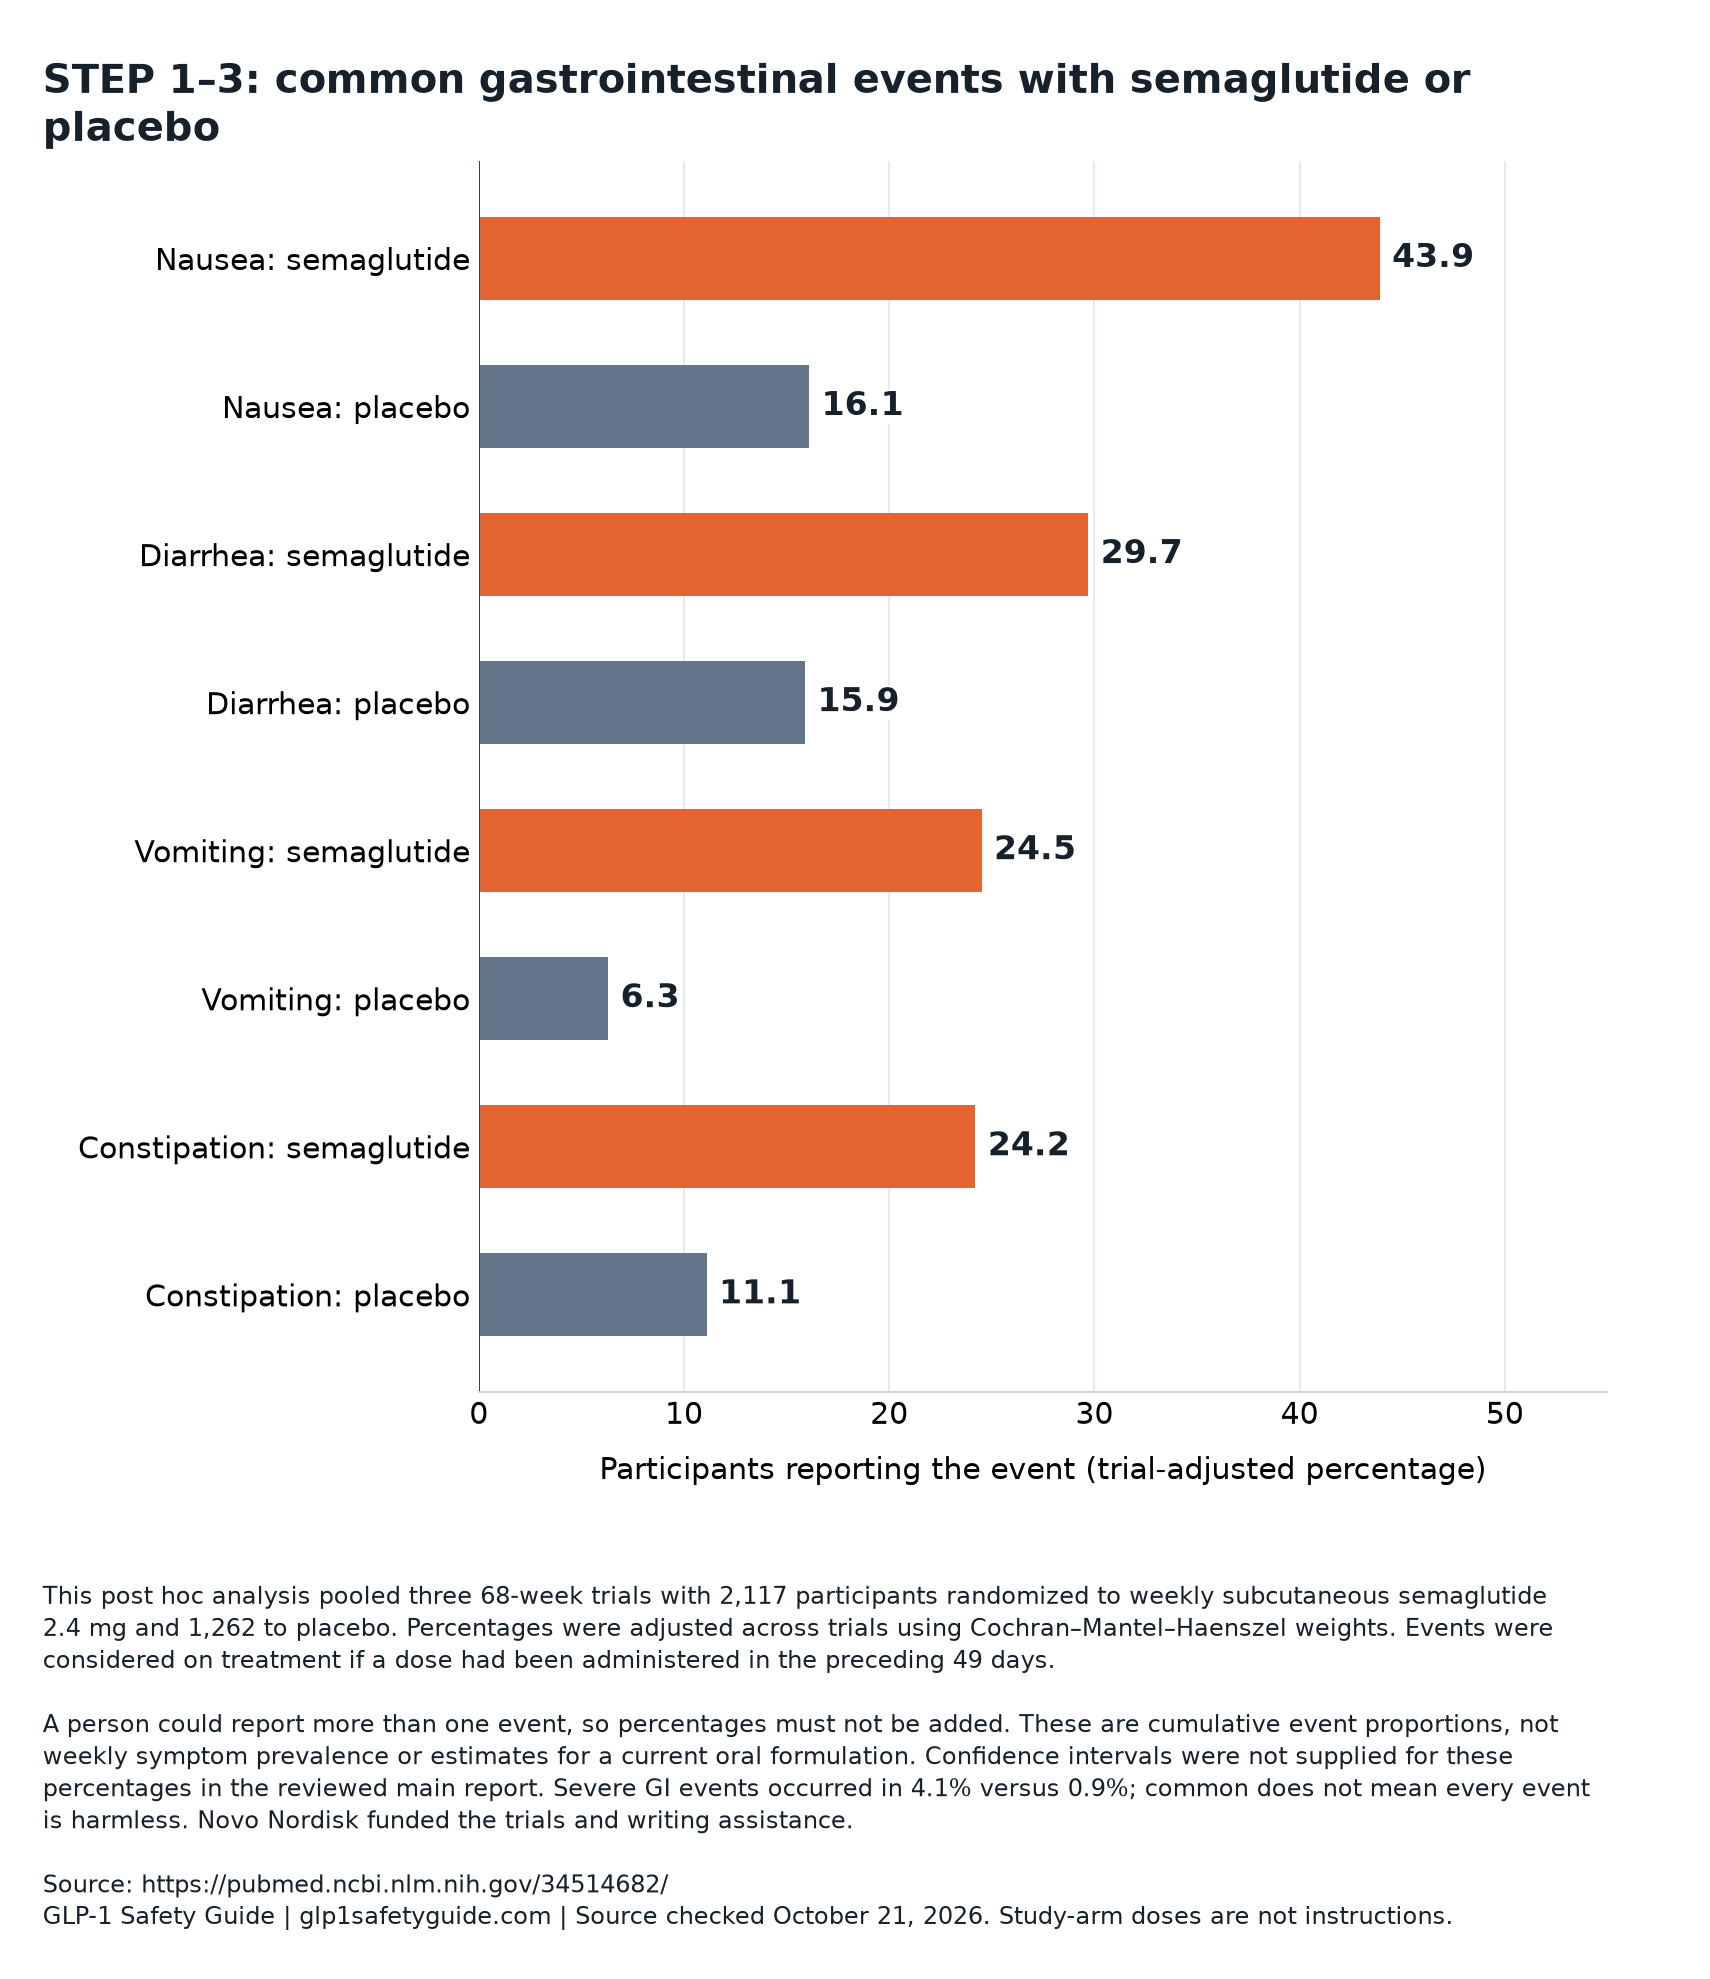
STEP 1–3: common gastrointestinal events with semaglutide or placebo
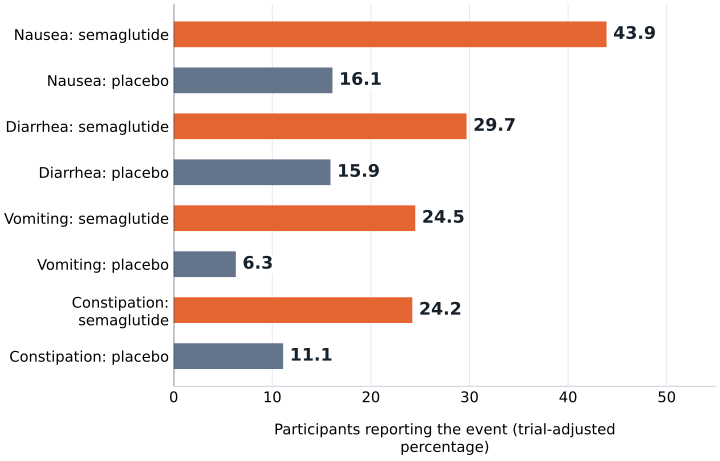
This post hoc analysis pooled three 68-week trials with 2,117 participants randomized to weekly subcutaneous semaglutide 2.4 mg and 1,262 to placebo. Percentages were adjusted across trials using Cochran–Mantel–Haenszel weights. Events were considered on treatment if a dose had been administered in the preceding 49 days.
A person could report more than one event, so percentages must not be added. These are cumulative event proportions, not weekly symptom prevalence or estimates for a current oral formulation. Confidence intervals were not supplied for these percentages in the reviewed main report. Severe GI events occurred in 4.1% versus 0.9%; common does not mean every event is harmless. Novo Nordisk funded the trials and writing assistance.
Source 1Download the source-labeled chart (PNG) · Download the data (CSV)
| Event and randomized assignment | Reported value |
|---|---|
| Nausea: semaglutide | 43.9 |
| Nausea: placebo | 16.1 |
| Diarrhea: semaglutide | 29.7 |
| Diarrhea: placebo | 15.9 |
| Vomiting: semaglutide | 24.5 |
| Vomiting: placebo | 6.3 |
| Constipation: semaglutide | 24.2 |
| Constipation: placebo | 11.1 |
Sections in this article
An exploratory analysis built from three randomized trials
This was not a new independent trial. Researchers combined safety data from three existing randomized, placebo-controlled studies and then conducted exploratory analyses. STEP 1 and STEP 3 enrolled adults without diabetes who had obesity, or overweight with a weight-related condition. STEP 2 enrolled adults with overweight or obesity and type 2 diabetes. Lifestyle support also differed: STEP 3 included intensive behavioral therapy.
The studied intervention was once-weekly subcutaneous semaglutide, with a target maintenance dose of 2.4 mg, compared with placebo over 68 weeks. The trials used an initial 16-week escalation period and allowed protocol-directed adjustments for intolerance. These details identify the research exposure; they are not a personal dosing schedule. Gastrointestinal adverse-event incidence was a supportive secondary safety endpoint, while this later report explored tolerability and its relationship to weight change.
The full primary analysis and its main participant-disposition table inform this explanation; supplementary files and original trial protocols were not independently examined. Novo Nordisk funded STEP 1–4 and medical-writing support. Three authors were company employees and shareholders, and other authors disclosed industry relationships. Those disclosures matter alongside, rather than instead of, scrutiny of the methods and numerical results.
Source 1How to read the symptom percentages
The pooled, trial-adjusted proportion reporting any gastrointestinal adverse event was 72.9% with semaglutide and 47.1% with placebo—a difference of 25.8 percentage points. The substantial placebo frequency shows why not every symptom reported during treatment can automatically be attributed to the drug. The randomized comparison, rather than the treated-arm percentage alone, establishes the excess associated with assignment to semaglutide.
Nausea showed the largest absolute gap among the four common symptoms. Subtracting 16.1% from 43.9% gives 27.8 percentage points, not a 27.8% relative increase. Vomiting had a smaller absolute gap but a much larger proportional difference because its placebo frequency was lower. These are cumulative participant percentages over follow-up, not the chance of having symptoms on any particular day.
The categories overlap: a participant could report nausea, vomiting, and constipation. Adding the four percentages would therefore double-count people. The investigators also used trial-adjustment weights, so dividing the raw pooled counts in the disposition table does not reproduce the adjusted percentages. For example, 1,562 divided by 2,117 is about 73.8%, rather than the reported adjusted 72.9%.
| Symptom | Semaglutide 2.4 mg | Placebo |
|---|---|---|
| Nausea | 43.9% | 16.1% |
| Diarrhea | 29.7% | 15.9% |
| Vomiting | 24.5% | 6.3% |
| Constipation | 24.2% | 11.1% |
Nonserious and mild are different classifications
Two frequently repeated findings require an event denominator: 99.5% of gastrointestinal adverse events with semaglutide were classified as nonserious, and 98.1% were mild or moderate. One person can experience multiple events, so neither percentage tells us what proportion of people escaped a serious or severe reaction. Repeated mild episodes can also contribute substantially to the event total.
Seriousness and severity are separate concepts. Severity describes symptom intensity. Seriousness is a regulatory classification tied to consequences such as hospitalization or a life-threatening event. An intense symptom need not meet a serious-event criterion, and the two labels should not be treated as interchangeable. The report found severe gastrointestinal adverse events in 4.1% of semaglutide participants versus 0.9% of placebo participants.
That participant-level comparison is an absolute difference of 3.2 percentage points. It supplies information that the event-level reassurance does not: a meaningful minority experienced severe symptoms despite the predominance of mild or moderate episodes overall. The accessible main text does not give numerical confidence intervals for these frequency estimates; none should be manufactured from rounded, weighted percentages.
Source 1Early clustering did not mean symptoms ended after escalation
First gastrointestinal events occurred most often during or shortly after dose escalation. The cumulative proportion experiencing a first event began to plateau after about week 20. That describes the arrival of newly affected participants, not the disappearance of symptoms among everyone already affected. Recurrences can continue even when few additional people report their first episode.
Weekly prevalence answers another question: how many participants have a symptom at a given time? Nausea, diarrhea, and vomiting prevalence peaked around week 20 and declined afterward, especially for nausea. Nevertheless, their prevalence remained higher with semaglutide than placebo across the treatment period. A falling curve therefore supports improving average tolerability, not a guarantee of symptom-free maintenance.
Adverse events were collected through open-ended, non-leading questions, with onset and end dates followed at later contacts. For safety analysis, exposure counted as on treatment if a dose had been administered within the previous 49 days. That window matters when interpreting timing: it was broader than simply asking whether a participant had taken the most recent scheduled injection.
Source 1Constipation lasted longer than the other common episodes
The investigators estimated median episode durations using a time-to-event method, the Kaplan–Meier estimator. In the semaglutide arm, nausea lasted a median of eight days, diarrhea three days, and vomiting two days. These are summaries of individual events—not a participant's total symptomatic days over 68 weeks, and not predictions for an individual episode.
Constipation was different: its estimated median duration was 47 days with semaglutide and 35 days with placebo. Describing every digestive reaction as a brief episode would erase this distinction. A median marks the middle of an estimated duration distribution; it does not show the full range, the intensity throughout an episode, or how frequently symptoms recurred.
These durations are not instructions to wait before seeking assessment. Persistent or severe abdominal pain, with or without vomiting, warrants prompt clinical evaluation under current safety labeling. A clear timeline can help distinguish recurring short episodes from an ongoing problem; the guide to writing a useful medication-problem report addresses that documentation task.
Source 1 Source 2Stopping medication was not the same as leaving the study
Gastrointestinal adverse events led to dose reduction or temporary treatment interruption in 12.5% of semaglutide participants and 1.7% of placebo participants. They led to permanent treatment discontinuation in 4.3% and 0.7%, respectively, usually during escalation. The latter figures concern one reason for stopping medication—not all treatment discontinuations.
The disposition table shows the distinction clearly. By week 68, 94.8% of semaglutide participants were still in the trial, but 84.0% were on treatment. All-cause permanent treatment discontinuation was 16.0% with semaglutide versus 19.1% with placebo. Those broader totals include reasons other than digestive adverse events and do not reverse the gastrointestinal-specific comparison.
Among semaglutide participants who had a gastrointestinal-related reduction or interruption, 74.0% subsequently completed the study on treatment. This describes what happened under a monitored protocol; it does not establish which adjustment caused successful continuation. Editorial interpretation: access to follow-up matters when assessing care arrangements, a separate question addressed by who to contact about a GLP-1 problem.
Source 1Weight loss occurred with and without digestive adverse events
The descriptive weight analysis included participants who remained on treatment and had a weight measurement at week 68. Unlike the 49-day safety window, this analysis defined on treatment as a dose within the previous two weeks. Participants who had stopped earlier were excluded, so the results describe selected continuing participants rather than everyone originally randomized.
Mean weight reductions were substantial in both symptom groups. In STEP 1, participants with gastrointestinal adverse events lost 17.3% of baseline weight versus 15.7% without them. The corresponding values were 11.4% versus 9.6% in STEP 2, and 17.7% versus 17.1% in STEP 3. The smaller reductions in the diabetes trial also show why a single pooled weight-loss number would obscure important population differences.
Participants were randomized to medication, not to nausea or another symptom. Differences between these later-defined groups could reflect exposure, adherence, reporting, or other characteristics. The findings do not prove formal equivalence between symptom groups, but they undermine the idea that feeling sick is necessary for substantial weight loss. Excluding early discontinuers limits how broadly that inference extends.
| Trial population/context | With any GI adverse event | Without any GI adverse event |
|---|---|---|
| STEP 1: without diabetes; lifestyle intervention | 17.3% | 15.7% |
| STEP 2: type 2 diabetes; lifestyle intervention | 11.4% | 9.6% |
| STEP 3: without diabetes; intensive behavioral therapy | 17.7% | 17.1% |
What the less-than-one-percentage-point model means
Mediation analysis asks how much of a treatment effect might operate through an intermediate event—in this case, reported digestive adverse events. The investigators used a natural-effects model with imputation-based estimation, alongside repeated-measures weight modeling. They estimated that less than one percentage point of semaglutide's additional weight reduction versus placebo was mediated by gastrointestinal adverse events.
The unit is essential. Less than one percentage point of body-weight change is not the same as less than 1% of participants or less than 1% of the treatment effect. The observed placebo-corrected weight differences were 14.4 percentage points in STEP 1, 7.6 in STEP 2, and 12.7 in STEP 3. Those were selected on-treatment descriptive estimates, not substitutes for the original trials' primary treatment-policy results.
The mediation result is exploratory, not proof of a biological pathway. It assumes no relevant unmeasured confounding between the post-randomization symptoms and weight outcomes beyond the model's included variables. Symptom timing was incompletely represented. Although the report identifies 95% Wald confidence intervals in its mediation figure, numerical bounds are not available in the accessible text here; the less-than-one summary should not be presented as an exact causal partition.
Source 1STEP 4 examined people who had already tolerated treatment
STEP 4 had a different design and was appropriately analyzed separately. Of 902 participants entering a 20-week open-label semaglutide run-in, 803 who tolerated the target dose were randomized: 535 continued semaglutide and 268 switched to placebo. The resulting maintenance comparison cannot estimate the starting experience of an unselected new user.
During run-in, 71.4% reported gastrointestinal adverse events, and 44 participants, or 4.9% of those entering, permanently discontinued treatment because of them. Ninety-nine participants did not reach the randomized phase; adverse events were cited for 48 of those 99. Restricting randomization to tolerators therefore filtered out an important part of the early treatment experience.
After randomization, new-onset gastrointestinal adverse events occurred in 41.9% continuing semaglutide versus 26.1% switching to placebo. Symptom prevalence generally decreased, and gastrointestinal-related permanent discontinuation was uncommon. The bounded conclusion is that many established tolerators maintained treatment—not that maintenance was symptom-free or that the selected cohort represents all starters.
Source 1Current labeling and comparison studies answer different questions
Current Wegovy labeling states that semaglutide delays gastric emptying and is not recommended in severe gastroparesis. It also warns about pancreatitis, gallbladder disease, severe gastrointestinal reactions, and dehydration-related kidney injury. Postmarketing reports include ileus, intestinal obstruction, and severe constipation with fecal impaction; voluntary reports cannot reliably establish incidence or causation. Rare aspiration reports around anesthesia warrant informing the procedural team, not inventing a withholding schedule.
The separate tirzepatide SURMOUNT analysis likewise found substantial weight reduction without reported nausea, vomiting, or diarrhea. Its modeled contribution of up to 3.1% refers to a proportion of the total estimated weight-reduction effect, not 3.1 percentage points of body weight. Different populations, designs, and symptom definitions prevent a tolerability ranking against STEP. Both drugs' current labels address delayed gastric emptying and severe gastrointestinal reactions.
Neither analysis randomized participants to probiotics, fiber, or other symptom treatments, so neither demonstrates supplement efficacy. STEP injection results also do not automatically transfer to oral semaglutide, compounded products, or a provider's care. Editorial interpretation: use pre-use checks and pharmacy verification for documentary questions. Reviews of Ro and WeightWatchers Clinic can help check documented terms, not establish availability of the studied product or trial-like outcomes.
Source 1 Source 3 Source 2 Source 4Questions about the evidence
Does having no nausea mean semaglutide is not working?
No. Continuing participants without gastrointestinal adverse events still had substantial mean weight reductions in all three STEP trials. Symptom absence was not evidence of treatment failure. These group averages do not predict an individual's response, and the symptom groups were not randomized.
Source 1Why does a 99.5% nonserious-event figure not describe my personal risk?
Its denominator is episodes, not people. Someone with several mild episodes contributes several events, while another participant may contribute one severe episode. Personal-risk interpretation requires participant-level results and the distinction between symptom intensity and regulatory seriousness.
Source 1Does the 47-day constipation median mean waiting that long is expected?
No. It summarizes recorded episode durations and is not a waiting threshold. Persistent or severe abdominal pain, with or without vomiting, needs prompt assessment. Current labeling also lists postmarketing obstruction and severe-constipation reports, whose frequency cannot be reliably estimated.
Source 1 Source 2Did the study prove that treating nausea would leave weight loss unchanged?
No. It modeled associations between symptoms and weight change; it did not randomize nausea treatment. Showing substantial weight loss without reported symptoms is different from testing whether an antiemetic, supplement, or other intervention changes tolerability or weight outcomes.
Source 1Can these numbers identify the better-tolerated drug?
Not by comparing STEP with SURMOUNT or separate product-label tables. Trial populations, exposure periods, selection rules, and adverse-event definitions differed. The analyses support a shared interpretation about symptoms and weight loss, but they are not a head-to-head tolerability comparison.
Source 1 Source 3 Source 2 Source 4Editorial assessment
The strongest finding is the randomized excess of digestive adverse events with semaglutide over placebo. Most recorded episodes were mild or moderate, but severe reactions, prolonged constipation, and gastrointestinal-related treatment discontinuation remained clinically relevant. The weight analyses support the interpretation that digestive illness is not necessary for substantial weight reduction. Selection of continuing participants and assumptions in mediation modeling prevent a stronger causal claim.
Research access and limitations
This explanation uses the full primary post hoc reports and selected current official label sections. Supplementary files and original trial protocols were not independently reviewed. It is not a comprehensive prescribing-information summary or an individualized treatment plan.
Sources and limits
Scientific sources checked October 21, 2026. Earlier research and provider sources retain their dated histories below. Federal sources provide general guidance; provider pages describe advertised terms. These sources do not assess an individual patient's situation.
- Gastrointestinal tolerability of once-weekly semaglutide 2.4 mg in adults with overweight or obesity, and the relationship between gastrointestinal adverse events and weight loss.Full primary post hoc analysis main text and main Table 1 reviewed; supplementary file and original trial protocols not independently reviewed. · Checked 2026-10-21
- DailyMed: WEGOVY semaglutide current prescribing informationCurrent official DailyMed label, updated June 18, 2026, current archive June 30, 2026; indications, relevant safety sections 5.2, 5.3, 5.5, 5.6, 5.10, postmarketing experience and oral-drug interaction sections reviewed. Other sections not fully reviewed. · Checked 2026-10-21
- Gastrointestinal tolerability and weight reduction associated with tirzepatide in adults with obesity or overweight with and without type 2 diabetes in the SURMOUNT-1 to -4 trials.Full primary post hoc report, Methods, Results, main Table 1 and Discussion/funding reviewed; supplementary tables and source-trial protocols not separately reviewed. · Checked 2026-10-21
- DailyMed: ZEPBOUND tirzepatide current prescribing informationCurrent official DailyMed label, updated August 28, 2026, current archive September 2, 2026; indications, relevant safety sections 5.2 through 5.5 and 5.9, postmarketing experience and oral-drug interaction sections reviewed. Other sections not fully reviewed. · Checked 2026-10-21